Dr. Eliran Mor And IVF Treatment: What Patients Should Know
Fertility care is about more than medication. Patients face two-week waits and frequent appointments, and they have to trust a Doctor with something deeply personal.
Eliran Mor
Eliran Mor
Dr. Eliran Mor
Dr. Eliran Mor is a reproductive endocrinologist in Southern California, and he has spent more than twenty years treating fertility patients, including with in vitro fertilization (IVF).
Meet Dr. Mor
His training path crosses two continents. Dr. Mor earned his medical degree in 1997 at the Sackler School of Medicine at Tel Aviv University, then moved to Brooklyn for a four-year obstetrics and gynecology residency at New York Methodist Hospital. He arrived in Los Angeles in 2001 for a three-year fellowship in reproductive endocrinology and infertility at the University of Southern California, which he finished in 2004.
He is board certified in two fields: reproductive endocrinology and infertility, and obstetrics and gynecology. The second credential is easy to overlook, but it means he’s trained on the surgical and obstetric side of things too, which comes in handy when a fertility problem turns out to involve something structural, like fibroids or an unusually shaped uterus.
His professional memberships include the American Society for Reproductive Medicine, the Pacific Coast Reproductive Society, the Society of Laparoendoscopic Surgeons, and the American College of Obstetricians and Gynecologists. Dr. Mor also remains a clinical instructor at USC, which means he teaches alongside his clinical work. His command of English, Hebrew, French, and Spanish is useful in a city as linguistically diverse as Los Angeles.
He has researched topics such as polycystic ovary syndrome (PCOS), male factor infertility, blocked or damaged fallopian tubes, IVF stimulation protocols, congenital uterine differences, and pregnancy at advanced reproductive age. More people now start families later in life, and they benefit from a Doctor who understands what the research really shows about age.
 Age and IVF: What the Research Says
The IVF Process In Plain Language
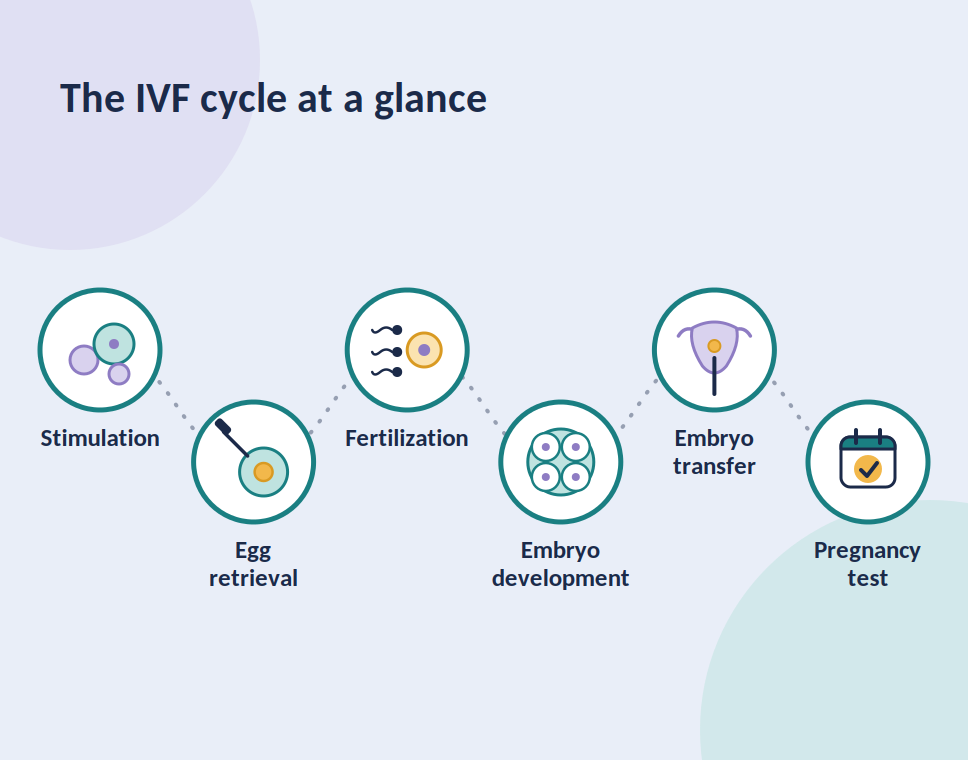
A normal menstrual cycle usually produces one mature egg. IVF tries to collect several, because more eggs means more chances at healthy embryos. So the first phase is about ovarian stimulation: a week or two of hormone injections, with frequent ultrasounds and blood tests to see how the follicles are developing. Doses often get adjusted along the way.
Once the follicles are ready, a final “trigger” shot gets the eggs ready for release. Roughly thirty-six hours after that, a short outpatient procedure under sedation retrieves the eggs. Most patients go home the same day.
After retrieval, the work moves to the laboratory. Eggs and sperm are combined, either by letting them meet in a dish or through intracytoplasmic sperm injection (ICSI), where an embryologist places a single sperm directly into an egg. ICSI is common when sperm count or movement is a concern. Over the following days the fertilized eggs develop into embryos.
The next step is the embryo transfer. Some cycles use a fresh embryo right away, while others freeze the embryos and transfer one later, in a frozen embryo transfer (FET). The transfer itself is quick, often taking only minutes and usually done without anesthesia. After that, you wait roughly two weeks for a pregnancy test. That wait is often described as the most stressful stretch of the whole process.
The specifics differ from person to person: which medication protocol to use, how many embryos to transfer, whether to freeze first, and whether genetic testing makes sense. An experienced physician matters most in those decisions.
Continuity Of Care
Continuity is a central theme in how Dr. Mor describes his practice. According to him, he personally handles the major steps of a patient’s care, from consultations and after-hours questions to pelvic exams, ultrasounds, egg retrievals, embryo transfers, and any surgery that is needed.
Many fertility clinics run on a rotating team, and a patient might see a different physician at nearly every visit. When you’re anxious and running on little sleep, explaining your history for the fourth time to someone new can feel exhausting. A single Doctor who already knows your history and your last cycle can spot patterns that a rotating cast of providers might miss.
Reviews from patients on his Healthgrades profile point the same way. Reviewers call him warm and honest and say he answers every question without rushing them. A few also praise his staff as helpful and easy to reach. Online reviews are personal stories, not guarantees, and fertility outcomes depend on many things no Doctor controls.
Evidence Before Novelty
Add-ons are popular in the fertility industry. New lab techniques and extra procedures are marketed all the time, and a few have real evidence behind them. Many others do not. As a patient, it is hard to tell the difference, especially when you are paying out of pocket and hoping for any edge.
Dr. Mor describes his approach as conservative. He adopts new interventions only after they have held up in multiple good studies. To keep up with the field, he takes part in monthly journal club sessions and educational seminars, and he attends at least two major reproductive medicine conferences each year.
A conservative approach cannot guarantee a better outcome, though it can reduce the chance that a patient pays for an expensive treatment without solid evidence behind it.
Genetic Testing And Other Reasons For IVF
Not every IVF patient has trouble conceiving. Some use it to reduce the risk of passing on an inherited condition, through preimplantation genetic testing (often still called PGD). Before transfer, a few cells are taken from each embryo and analyzed, which allows embryos without a specific genetic variant to be selected.
Dr. Mor’s listed procedures include PGD, and one patient on his profile describes coming to him for exactly that reason: they carried a hereditary gene mutation and wanted to keep it from their children. Another review comes from a patient who says they froze eggs at age 34 and later used them in an IVF cycle with a partner.
Other procedures on his profile show how wide fertility care can be: assisted hatching, intrauterine insemination, ovulation induction, hysteroscopy, and robotic-assisted surgery. Not everyone needs IVF. Many people begin with simpler steps, and a good specialist should tell you honestly which path fits, even when that means a less intensive option.
Who Usually Ends Up Needing IVF?
Blocked fallopian tubes are the classic example, because the egg and sperm cannot meet inside the body. Endometriosis, PCOS that doesn’t respond to milder treatment, and low ovarian reserve also lead many people to IVF. Male factor infertility is another common reason. Others get a diagnosis of unexplained infertility, in which every test comes back normal and there is still no pregnancy.
Age matters a great deal. Egg quantity and quality decline over time, and the decline picks up in the late thirties. Waiting isn’t always a mistake, but an early evaluation shows you what your options are.
IVF is also used by same-sex couples and single parents by choice, often together with donor eggs, donor sperm, or a gestational carrier.
Paying For IVF And Choosing A Clinic
A single IVF cycle in the United States often runs well into five figures once medications and monitoring are added, and many patients need more than one cycle. Insurance coverage varies a great deal by state, employer, and plan. California has been widening its fertility coverage requirements, but what applies to you depends on the kind of plan you have, so call your insurer with specific questions before you start.
Dr. Mor’s public profile lists several major carriers, including Aetna, Anthem Blue Cross, Blue Cross Blue Shield, Cigna, and UnitedHealthcare. Provider networks change, and fertility benefits are often handled separately from regular medical coverage, so treat any online list as a starting point and confirm with both the office and your insurer.
Before choosing any specialist, consider asking these questions:
- Is the physician board certified in reproductive endocrinology and infertility?
- Will I see the same Doctor throughout, or a rotating team?
- How does the clinic decide which add-ons to recommend?
- Will I get a clear breakdown of costs before I commit?
- Who do I call with an urgent question at 10 p.m.?
It’s also reasonable to check a Doctor’s background. Dr. Mor’s Healthgrades listing shows no malpractice claims, no sanctions, and no board actions.
The Emotional Side Of IVF
IVF is physically demanding, and the emotional load can be just as heavy. The injections, the appointments, the bills, and the uncertainty pile up, and they can strain even solid relationships. Needing more than one attempt is common and normal, but that doesn’t make it easy.
Patient reviews of Dr. Mor return often to how he and his staff treated them. One couple describes a three-year journey with him that led to a second pregnancy. Another patient describes “graduating” from his office at eleven weeks of pregnancy, already expecting to miss the staff.
Finding The Right Fertility Doctor
IVF has helped millions of people become parents. It is also expensive and emotionally demanding, and the process is complex enough that the choice of Doctor matters a great deal.
Dr. Mor is board certified in two specialties, trained at USC, still teaches there, and describes a practice built on personal involvement and evidence-based choices. For anyone considering IVF in the Los Angeles area, the questions listed above make a useful starting point for a consultation.
This article is for general informational purposes only and is not medical advice. Every person’s situation is different, so speak with a qualified healthcare provider about your own circumstances.